Pancreatitis: Causes, Warning Signs, and When It Becomes an Emergency
Home » Media » Pancreatitis: Causes, Warning Signs, and When It Becomes an Emergency
October 23, 2026
At a Glance
Overview
Details
Condition
Pancreatitis (inflammation of the pancreas)
Main types
Acute pancreatitis and chronic pancreatitis
Common causes
Gallstones, alcohol consumption, high triglyceride levels and certain medications
Typical symptoms
Upper abdominal pain, pain extending to the back, nausea and vomiting
Emergency warning signs
Sudden severe abdominal pain, persistent vomiting, fainting, breathing difficulties or signs of serious infection
Diagnosis
Clinical assessment, pancreatic enzyme blood tests and imaging when indicated
Treatment
Hospital monitoring, intravenous fluids, pain relief, nutritional support and treatment of the underlying cause
Possible complications
Pancreatic necrosis, infected collections, organ failure and, in chronic disease, digestive problems or diabetes
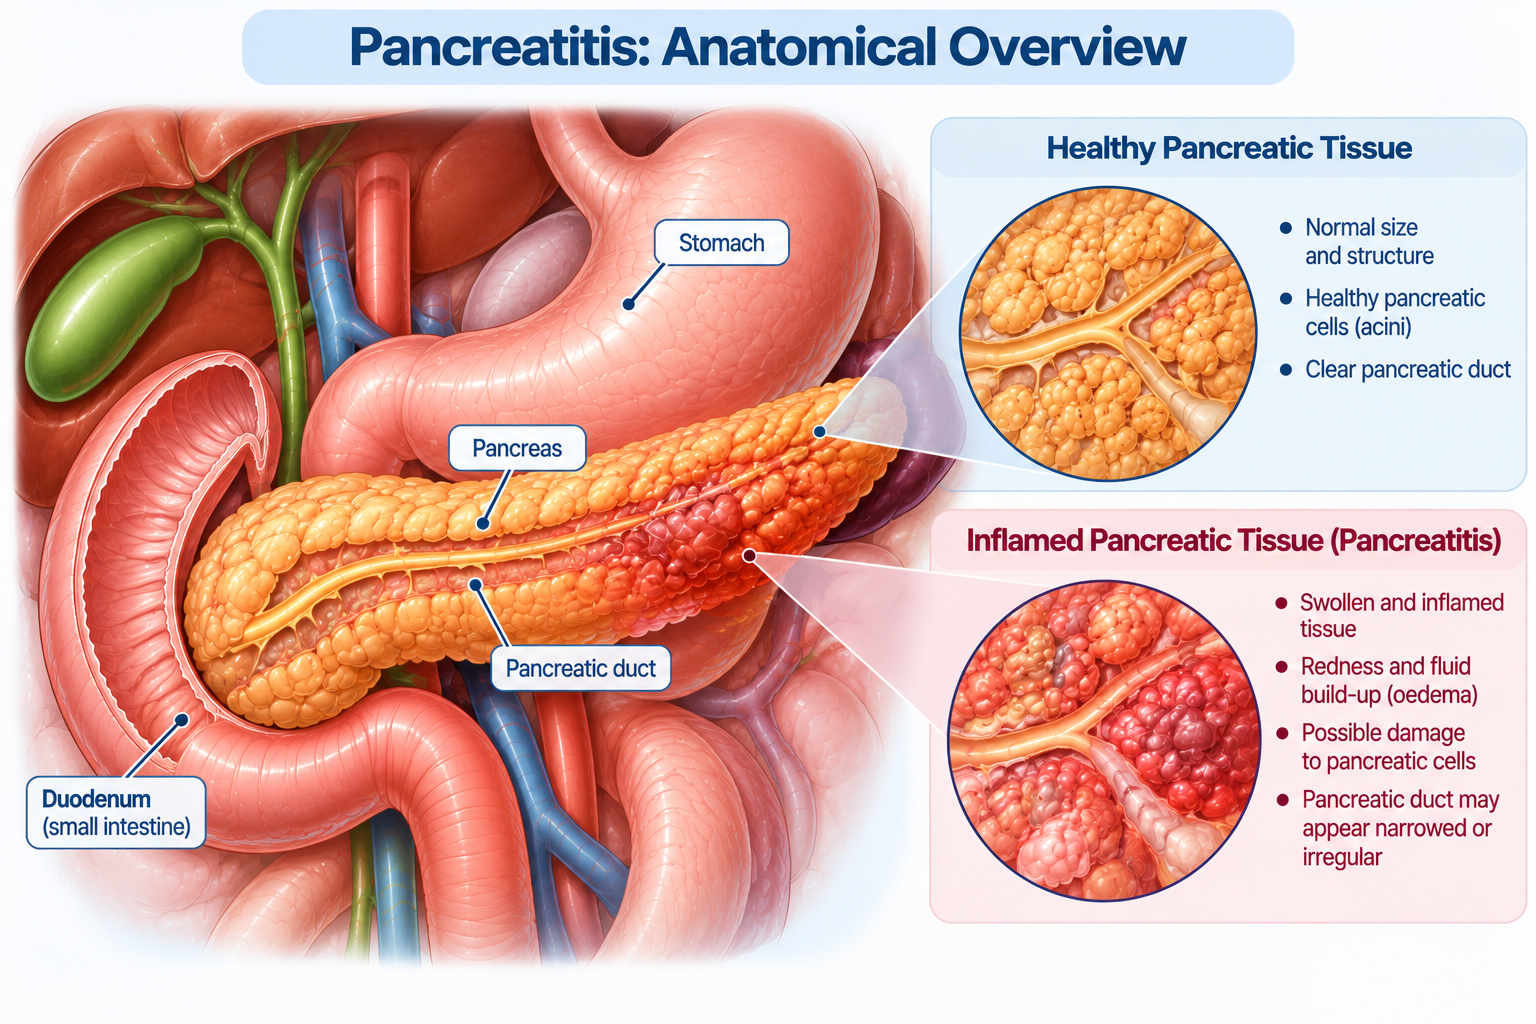
Pancreatitis is inflammation of the pancreas that can cause swelling, tissue damage and disruption of its normal digestive functions.
Pancreatitis is an inflammatory condition affecting the pancreas that can range from a relatively mild illness to a life-threatening medical emergency. It often begins with upper abdominal pain, sometimes accompanied by nausea and vomiting. Although these symptoms can resemble those of other digestive conditions, acute pancreatitis may worsen rapidly and, in severe cases, affect organs beyond the pancreas.
The causes and consequences of pancreatitis vary. Gallstones and alcohol consumption are among the most common triggers of acute pancreatitis, while other factors, including markedly elevated blood triglycerides, certain medications and abnormalities of the pancreatic or bile ducts, may also contribute. Some patients experience a single episode and recover, whereas others develop recurrent inflammation or chronic pancreatic damage that affects digestion and blood sugar regulation.
n this blog, we discuss what causes pancreatitis, how acute and chronic pancreatitis differ, which symptoms should not be ignored, how the condition is investigated and when pancreatitis requires emergency medical care.
What is Pancreatitis?
Pancreatitis is inflammation of the pancreas, an organ located behind the stomach that performs two essential functions. It produces digestive enzymes that help break down food in the small intestine and releases hormones, including insulin and glucagon, that regulate blood glucose levels.
Under normal circumstances, pancreatic digestive enzymes are produced and transported through the pancreatic duct before becoming fully active in the intestine. In acute pancreatitis, abnormal activation of digestive enzymes within the pancreas and other inflammatory processes can injure pancreatic tissue, producing swelling, pain and inflammation. In severe cases, the inflammatory response can extend beyond the pancreas and affect other organs.
Pancreatitis is broadly classified into two forms:
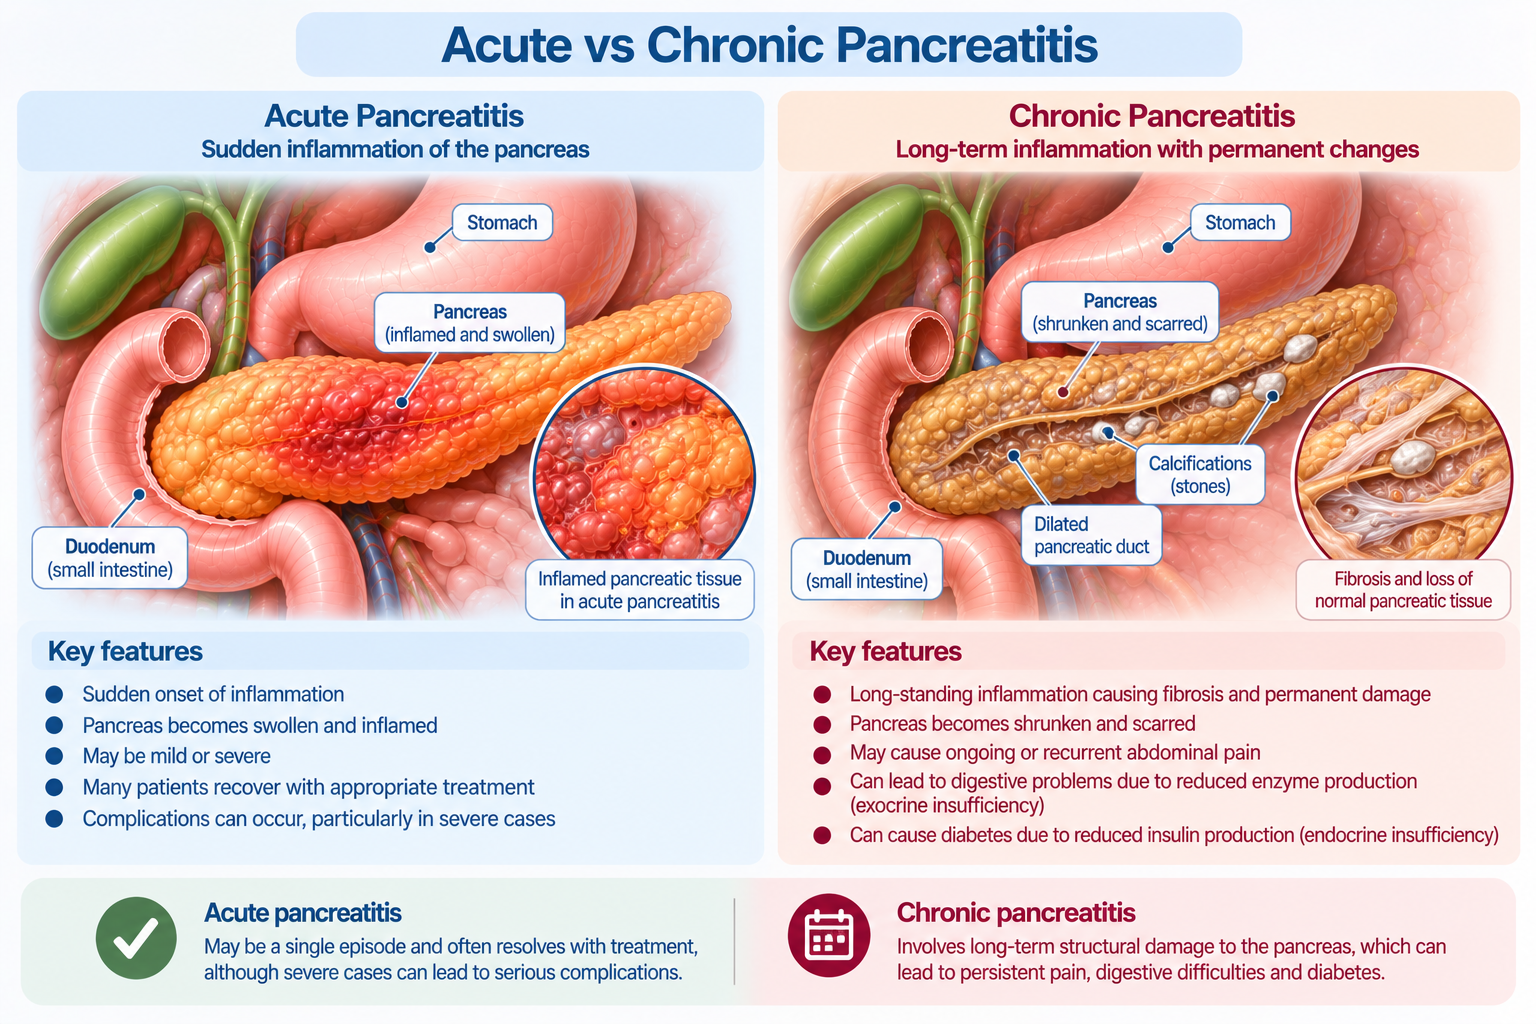
Acute pancreatitis — A sudden episode of pancreatic inflammation that develops over hours or days [1]. Many patients recover with appropriate treatment, although some develop serious local or systemic complications.
Chronic pancreatitis — A long-standing inflammatory condition characterised by progressive structural damage, fibrosis and potentially irreversible loss of pancreatic function [2]. It may cause persistent or recurrent pain, digestive difficulties and diabetes.
The distinction matters because acute pancreatitis requires assessment of the immediate severity and underlying cause, while chronic pancreatitis often involves longer-term management of pain, nutrition, pancreatic function and associated complications.
What Causes Pancreatitis?
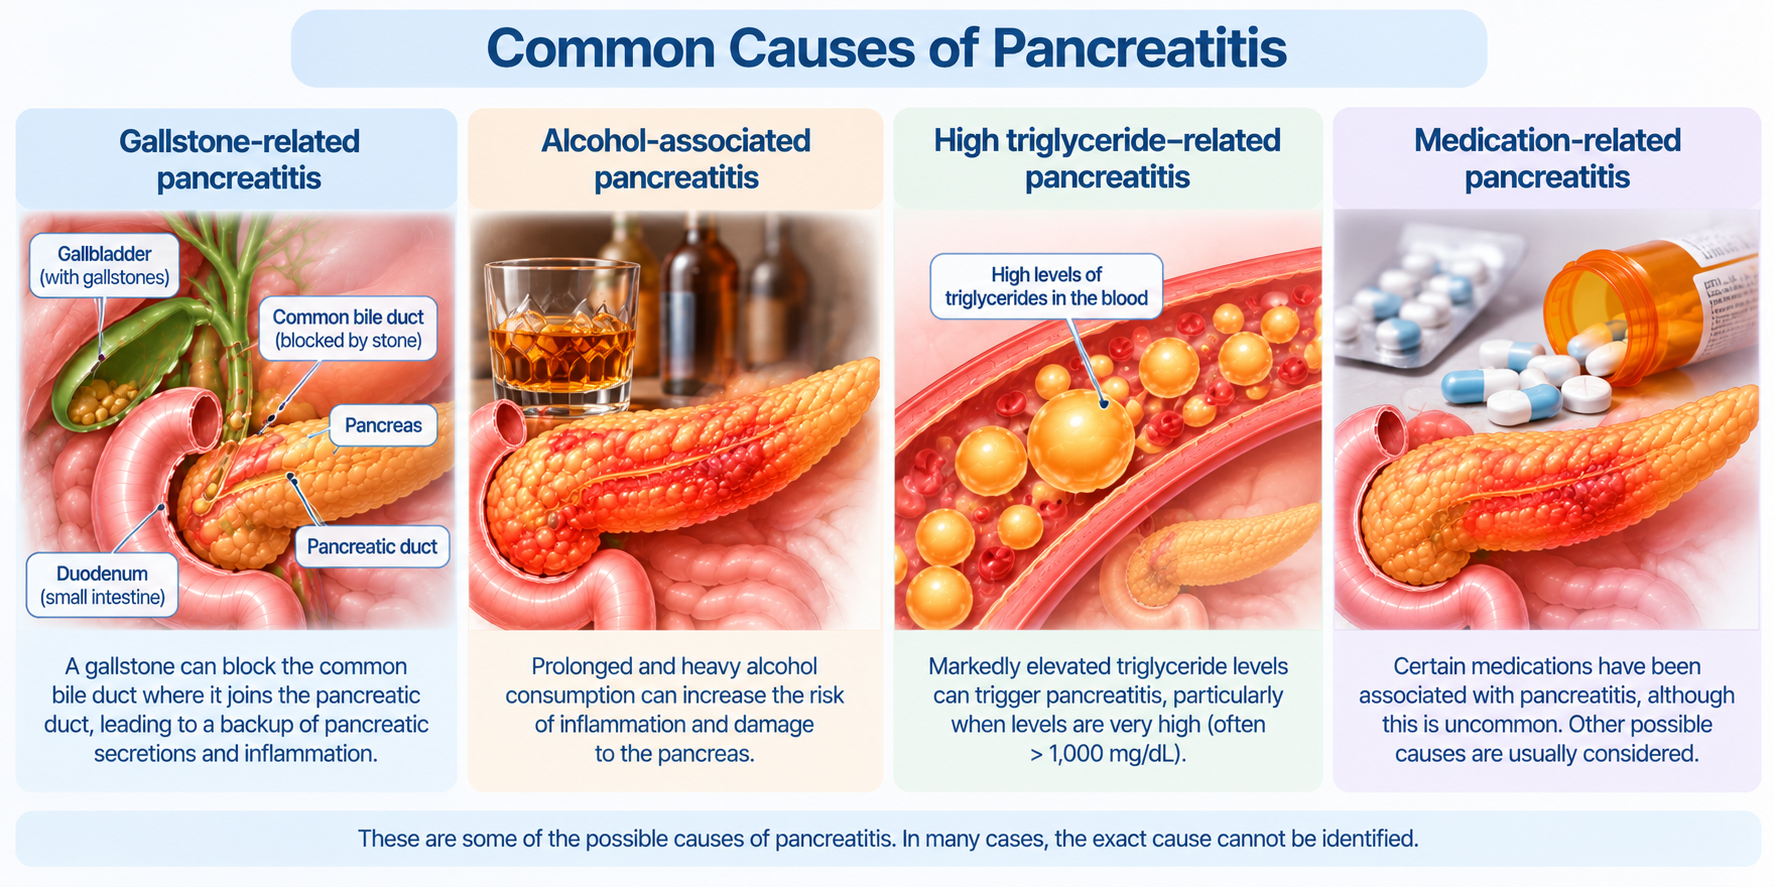
Pancreatitis can develop when digestive enzymes and inflammatory processes injure pancreatic tissue. Although gallstones and alcohol are among the leading causes, several other medical conditions and exposures can trigger inflammation.
Gallstones — Gallstones are a major cause of acute pancreatitis. A stone passing from the gallbladder into the common bile duct may temporarily obstruct the area where bile and pancreatic secretions drain into the small intestine. This can trigger pancreatic inflammation, even if the stone subsequently passes. Gallstone pancreatitis may occur in someone who has not previously experienced gallbladder symptoms [3].
Alcohol consumption — Heavy alcohol use is associated with both acute and chronic pancreatitis [4]. The risk generally increases with sustained excessive consumption, although individual susceptibility varies. Alcohol is an important cause to investigate, but pancreatitis should not automatically be attributed to alcohol simply because a patient drinks.
High triglyceride levels — Markedly elevated triglycerides, a type of fat found in the blood, can trigger acute pancreatitis [5]. This is particularly relevant when levels exceed approximately 1,000 mg/dL (11.3 mmol/L), although the clinical context and other potential causes must also be considered.
Certain medications — Some medicines have been associated with drug-induced pancreatitis [6]. However, establishing that a medication is responsible can be difficult, and other causes need to be excluded. Patients should not discontinue prescribed treatment without medical advice.
High blood calcium levels — Hypercalcaemia, particularly when pronounced, can contribute to pancreatic inflammation [7]. It may occur in association with conditions such as hyperparathyroidism.
Pancreatic duct abnormalities or obstruction — Structural abnormalities, duct narrowing or an obstructing lesion may interfere with pancreatic drainage [8]. In some patients, a pancreatic tumour may be responsible, particularly when pancreatitis develops without an obvious cause in an older adult.
Medical procedures, injuries and other conditions — Pancreatitis can occasionally follow abdominal trauma or endoscopic retrograde cholangiopancreatography (ERCP), a procedure used to investigate or treat problems involving the bile and pancreatic ducts. Autoimmune conditions, genetic factors and certain infections may also contribute.
In some cases, the cause remains unidentified after initial investigation. This is known as idiopathic pancreatitis. Further assessment may be appropriate, especially when episodes recur, because small gallstones, pancreatic duct abnormalities or other underlying conditions may not be apparent on the first examination.
Pancreatitis can develop due to gallstones, prolonged heavy alcohol consumption, markedly elevated triglyceride levels or certain medications, although the underlying cause is not always identifiable.
What are the Warning Signs of Acute Pancreatitis?
The most characteristic symptom of acute pancreatitis is pain in the upper abdomen. It may begin suddenly or develop over several hours and can range from moderate discomfort to severe, persistent pain. The pain frequently extends towards the back and may be accompanied by nausea, vomiting or abdominal tenderness.
Common symptoms include:
Upper abdominal pain — Often felt in the centre or upper part of the abdomen and may become persistent or severe.
Pain extending to the back — Some patients experience pain that appears to pass through the upper abdomen towards the back.
Nausea and vomiting — These frequently accompany an acute episode and may make it difficult to tolerate food or fluids.
Abdominal tenderness or swelling — The abdomen may become painful to touch or feel distended.
Fever — An elevated temperature can accompany pancreatic inflammation, although it may also indicate infection or another complication.
Rapid heartbeat — This may occur in association with pain, dehydration or a more extensive inflammatory response.
The symptoms of acute pancreatitis can overlap with gallbladder inflammation, peptic ulcer disease and other abdominal emergencies. Severe upper abdominal pain may also arise from conditions unrelated to the digestive system, including certain cardiovascular emergencies.
Persistent or severe upper abdominal pain, particularly when accompanied by repeated vomiting, requires urgent medical assessment rather than observation at home.
When Does Pancreatitis Become a Medical Emergency?
Acute pancreatitis can become life-threatening when inflammation extends beyond the pancreas and causes significant fluid loss, circulatory problems or dysfunction of major organs. Although many patients recover without developing severe complications, it is not always possible to determine how serious an episode will become from the initial pain or symptoms alone.
Emergency medical assessment is particularly important when abdominal pain is accompanied by signs that may indicate severe inflammation, dehydration, infection or organ dysfunction.
Warning Signs Requiring Emergency Assessment
Sudden, severe or rapidly worsening upper abdominal pain
Repeated vomiting or an inability to keep fluids down
Fainting, collapse, marked dizziness or confusion
Shortness of breath or difficulty breathing
Fever or chills accompanied by severe abdominal pain
Jaundice, especially when accompanied by fever or chills
A very rapid heartbeat with significant weakness or signs of dehydration
These symptoms may indicate acute pancreatitis, a serious complication or another abdominal emergency. Patients experiencing them should attend an emergency department promptly.
How is Mild Pancreatitis Different from Severe Pancreatitis?
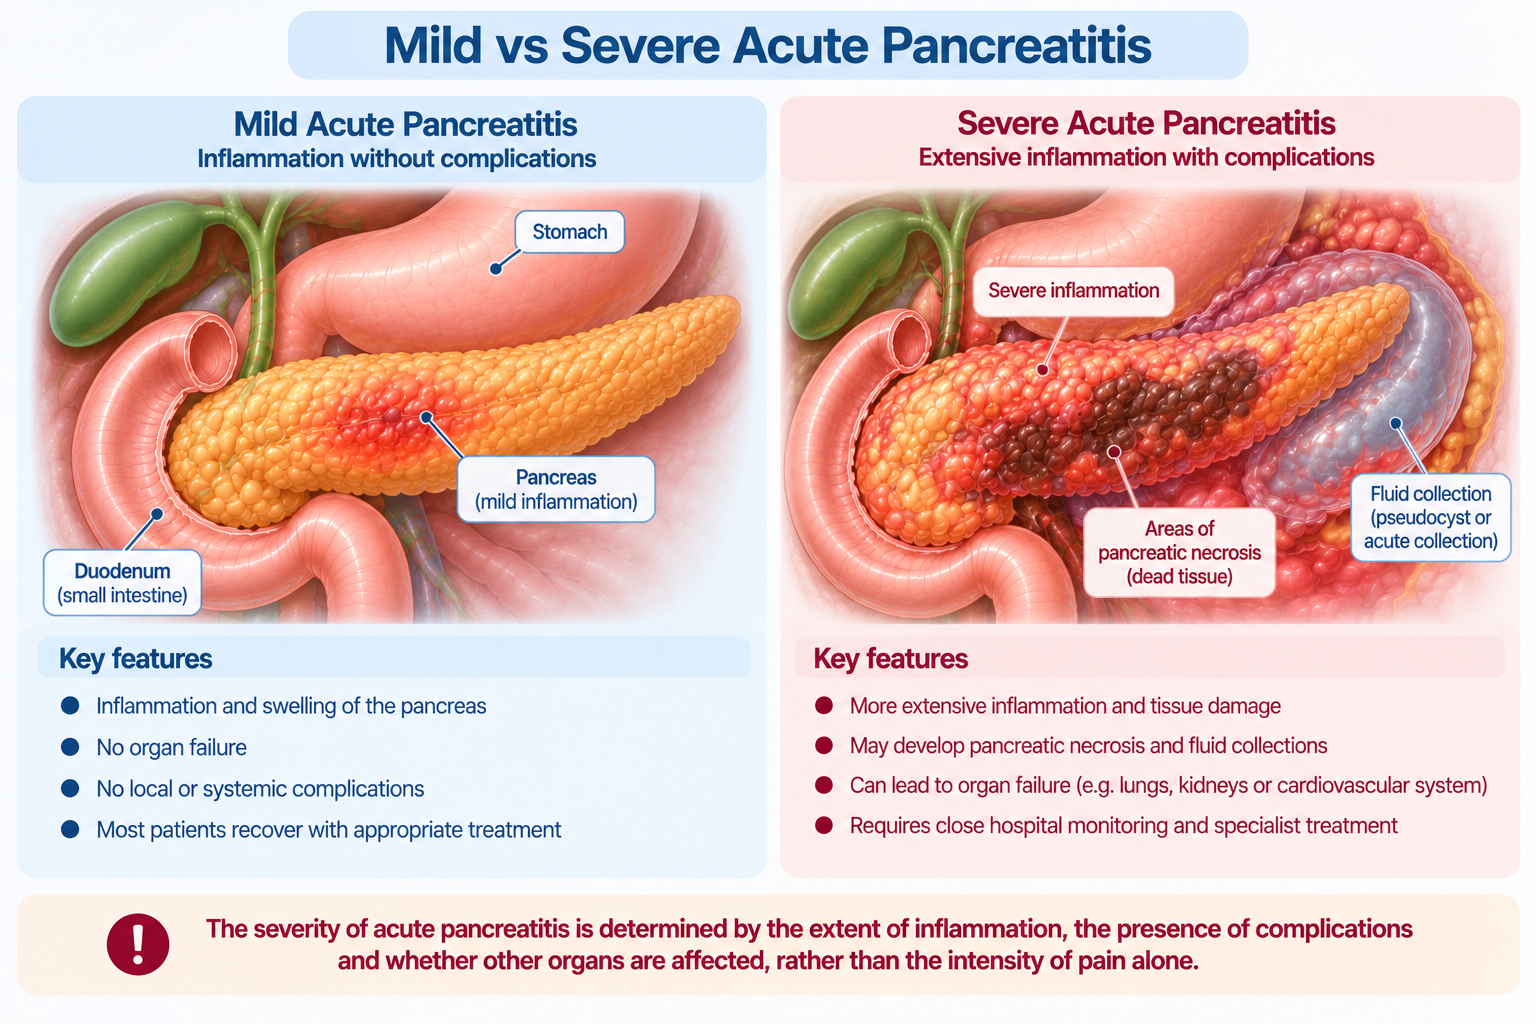
The severity of acute pancreatitis is determined by the extent of inflammation, the presence of complications and whether other organs are affected. Pain intensity alone cannot reliably distinguish a mild episode from a severe one.
Severity
Clinical Characteristics
Mild acute pancreatitis
No organ failure or local or systemic complications. Most patients recover with appropriate supportive treatment.
Moderately severe acute pancreatitis
Temporary organ failure lasting no longer than 48 hours, local or systemic complications, or both, without persistent organ failure.
Severe acute pancreatitis
Persistent organ failure lasting more than 48 hours, potentially involving the lungs, kidneys or cardiovascular system.
In severe pancreatitis, the inflammatory response can impair circulation, breathing or kidney function. Some patients also develop pancreatic necrosis, in which part of the pancreatic tissue loses its blood supply and becomes non-viable. Necrosis may remain sterile or become infected, creating additional treatment challenges [9].
The severity of an episode may not be fully apparent at presentation. Patients therefore require appropriate clinical assessment and, when admitted, reassessment during the early course of the illness to identify deterioration or developing complications.
Mild acute pancreatitis causes inflammation without organ failure or complications, while severe acute pancreatitis involves persistent organ failure and may be accompanied by pancreatic necrosis or fluid collections.
How is Acute Pancreatitis Diagnosed?
Diagnosis begins with an assessment of the patient’s symptoms, medical history and physical examination. Blood tests are used to look for evidence of pancreatic inflammation, while imaging may help establish the underlying cause or identify complications.
Acute pancreatitis is generally diagnosed when at least two of the following three criteria are present:
Abdominal pain characteristic of acute pancreatitis.
Blood lipase or amylase levels are at least three times the upper limit of normal.
Imaging findings consistent with acute pancreatitis.
Blood lipase is commonly used because it is a useful marker of pancreatic injury. However, elevated pancreatic enzymes are not specific to pancreatitis in every circumstance, and the results must be interpreted alongside the clinical findings.
Further investigations may include:
Blood tests — Liver blood tests may suggest gallstone-related obstruction, while triglyceride and calcium measurements can help identify other causes. Kidney function, blood counts and other tests help assess the patient's overall condition and possible complications.
Abdominal ultrasound — Ultrasound is particularly useful for identifying gallstones and assessing the gallbladder and bile ducts. It is often performed when acute pancreatitis is diagnosed because gallstones are a common underlying cause.
Contrast-enhanced CT — CT may be required when the diagnosis is uncertain, the patient is not improving as expected or complications are suspected. Routine CT is not necessary immediately for every patient with an otherwise clear diagnosis.
MRI and magnetic resonance cholangiopancreatography (MRCP) — These examinations may help assess the pancreatic and bile ducts, particularly when a retained bile duct stone or structural abnormality is suspected.
Endoscopic ultrasound (EUS) — EUS may be considered when further investigation is needed, particularly in patients with recurrent or unexplained pancreatitis.
The investigations are selected according to the clinical presentation. Their purpose is not only to confirm pancreatitis but also to establish its cause and determine whether complications or additional treatment are likely.
How is Acute Pancreatitis Treated in the Hospital?
Treatment of acute pancreatitis focuses on supporting the patient while the inflammation settles, identifying the underlying cause and managing any complications. The approach depends on the severity of the episode and the patient's response to initial treatment.
Intravenous fluid replacement — Pancreatic inflammation can cause substantial fluid shifts and dehydration. Intravenous fluids help maintain circulation and organ perfusion, particularly during the early stages [10]. The amount given must be reassessed regularly because excessive fluid administration can also cause harm, especially in patients with heart or kidney conditions.
Pain relief and symptom control — Appropriate pain medication is important because pancreatic inflammation can cause considerable discomfort. Treatment may also include medication for nausea and vomiting.
Nutritional support — Patients with mild acute pancreatitis are generally encouraged to resume oral feeding early, as tolerated, rather than remaining without food for a prolonged period. When oral intake is not possible, particularly in more severe cases, nutritional support through the digestive tract may be required.
Monitoring for complications — Clinical observations, blood tests and further imaging when indicated help identify dehydration, organ dysfunction, pancreatic necrosis or other complications. Patients with severe disease may require intensive care.
Treatment of the underlying cause — Management may include removing the gallbladder after gallstone pancreatitis, addressing a retained bile duct stone or treating severe hypertriglyceridaemia.
Antibiotics are not routinely prescribed simply because the pancreas is inflamed. They are used when there is an established or strongly suspected infection, such as infected pancreatic necrosis or associated cholangitis.
Most patients do not require pancreatic surgery during an uncomplicated acute episode. Procedures become relevant when there is a specific cause requiring intervention or when complications develop.
Why is Treating Gallstones Important After Gallstone Pancreatitis?
When pancreatitis is caused by gallstones, treating the acute inflammation is only part of the management. If the gallbladder remains in place, further stones may pass into the bile duct and trigger another episode.
For patients with mild gallstone pancreatitis who are suitable for surgery, laparoscopic cholecystectomy or keyhole gallbladder removal, is generally recommended during the same hospital admission, preferably before discharge. This reduces the risk of recurrent gallstone-related complications.
The timing may differ in patients with severe pancreatitis, pancreatic necrosis or significant fluid collections. In these circumstances, surgery may need to be delayed until the patient's condition and local inflammation have improved.
Some patients also require endoscopic retrograde cholangiopancreatography (ERCP). This procedure can be used to remove a stone obstructing the common bile duct or to relieve biliary obstruction. Urgent ERCP is particularly important when acute pancreatitis is accompanied by cholangitis, a potentially serious infection of the bile ducts.
What Complications Can Develop from Acute Pancreatitis?
Most patients with mild acute pancreatitis recover without lasting complications. However, severe inflammation can damage pancreatic tissue, affect surrounding structures or cause problems elsewhere in the body.
Important complications include:
Pancreatic necrosis — Severe inflammation may result in areas of pancreatic or surrounding tissue becoming non-viable. Necrosis can remain sterile or become infected. Infected necrosis is a serious complication that may require antibiotics and, in selected cases, drainage or removal of dead tissue.
Pancreatic fluid collections — Inflammatory fluid may accumulate within or around the pancreas. Some collections resolve spontaneously, while others persist or become symptomatic.
Pancreatic pseudocysts — A pseudocyst is a mature, encapsulated fluid collection that may develop after pancreatitis. Many do not require intervention, but treatment may be considered if a pseudocyst causes persistent symptoms, obstruction, infection or other complications.
Walled-off necrosis — This is an encapsulated collection containing necrotic pancreatic or surrounding tissue that typically develops several weeks after necrotising pancreatitis [11]. Its management differs from that of a simple pancreatic pseudocyst.
Infection — Infection of necrotic tissue or other associated collections may cause clinical deterioration and require specialist treatment.
Organ failure — Severe pancreatitis can impair lung, kidney or cardiovascular function. Persistent organ failure is the defining feature of severe acute pancreatitis and may require intensive care.
Not every collection or area of necrosis needs immediate drainage or surgery. In clinically stable patients, intervention for necrotic collections is often delayed, where possible, until the collection has matured and treatment can be performed more safely. The decision depends on infection, symptoms, obstruction and the patient’s overall condition.
What is Chronic Pancreatitis and How Does It Differ from Acute Pancreatitis?
Chronic pancreatitis is a long-standing inflammatory condition in which repeated or persistent injury leads to structural changes and fibrosis within the pancreas. Unlike a single episode of acute pancreatitis, chronic disease can progressively impair the organ’s ability to produce digestive enzymes and regulate blood glucose.
Some patients develop chronic pancreatitis following recurrent acute episodes, while others develop it through a combination of genetic, environmental, metabolic or autoimmune factors. Alcohol consumption and smoking are important modifiable risk factors, but chronic pancreatitis can also occur in people who do not drink alcohol.
Symptoms may include:
Recurrent or persistent upper abdominal pain, sometimes extending to the back
Pain that becomes worse after eating in some patients
Unintentional weight loss
Greasy, bulky or difficult-to-flush stools caused by fat malabsorption
Diarrhoea or other digestive difficulties
Diabetes resulting from reduced pancreatic hormone production
The digestive problems associated with chronic pancreatitis often develop when the pancreas can no longer produce sufficient digestive enzymes, a condition known as pancreatic exocrine insufficiency. Patients may require pancreatic enzyme replacement therapy to improve nutrient absorption, alongside dietary assessment and monitoring for nutritional deficiencies.
Chronic pancreatitis also increases the risk of pancreatic cancer, although most people with chronic pancreatitis do not develop it. New or changing symptoms, including unexplained weight loss, jaundice or a significant alteration in pain, should therefore be assessed rather than automatically attributed to the existing condition.
Acute pancreatitis causes sudden inflammation of the pancreas that may resolve with treatment, while chronic pancreatitis involves progressive, permanent damage that can lead to digestive difficulties and diabetes.
Can Pancreatitis Happen Again After Recovery?
Yes. Some people experience recurrent acute pancreatitis, particularly when the underlying cause has not been addressed. For example, untreated gallstones may trigger another episode, while continued heavy alcohol consumption or persistently elevated triglycerides can contribute to further pancreatic injury.
Preventing recurrence depends on identifying the cause and addressing any modifiable risk factors.
Treating gallstones — Gallbladder removal is commonly recommended after mild gallstone pancreatitis when the patient is suitable for surgery.
Avoiding alcohol — Abstinence is particularly important when pancreatitis is alcohol-related and is generally advised following an episode.
Stopping smoking — Smoking is associated with chronic pancreatic damage and may contribute to disease progression.
Managing triglycerides — Patients with severe hypertriglyceridaemia may require dietary changes, treatment of associated conditions and lipid-lowering medication.
Reviewing medications — When drug-induced pancreatitis is suspected, a clinician may assess whether an alternative treatment is appropriate.
Investigating unexplained episodes — Recurrent pancreatitis without an established cause may warrant additional imaging or specialist assessment.
An isolated episode does not necessarily lead to permanent pancreatic damage. However, recurrent attacks can increase the likelihood of chronic pancreatitis, making investigation and prevention important after recovery.
When Should You See a Pancreatic Specialist?
An acute episode of suspected pancreatitis requires prompt medical assessment, usually in a hospital setting. Specialist review becomes particularly relevant when the underlying cause is uncertain, episodes recur or complications require further investigation or intervention.
A hepatopancreatobiliary (HPB) specialist’s opinion may be appropriate when:
Pancreatitis is caused by gallstones and gallbladder surgery is being considered
There are recurrent episodes without a clearly identified cause
Imaging shows pancreatic necrosis, pseudocysts or other collections
A pancreatic or bile duct obstruction is suspected
Symptoms persist after the acute episode has resolved
Chronic pancreatitis is associated with significant pain or complications
A pancreatic lesion or other structural abnormality requires further assessment
Endoscopic, radiological or surgical treatment may be necessary
The purpose of specialist assessment is to determine whether further investigation or intervention is required. Not every patient with pancreatitis needs surgery, and many recover with supportive treatment and appropriate management of the underlying cause.
Key Takeaway
Pancreatitis can range from a short-lived inflammatory episode to a severe illness involving pancreatic tissue damage and organ failure. Gallstones and alcohol are among the leading causes, although metabolic conditions, medications, pancreatic duct abnormalities and other factors may also contribute.
The most characteristic symptom is upper abdominal pain that may extend towards the back, often accompanied by nausea or vomiting. Acute pancreatitis requires prompt medical assessment, and sudden severe pain, persistent vomiting, breathing difficulties, fainting, confusion or jaundice accompanied by fever should never be ignored.
Hospital treatment focuses on fluid replacement, pain control, nutritional support, monitoring for complications and addressing the underlying cause. In gallstone pancreatitis, gallbladder removal or selected bile duct procedures may be necessary to reduce the risk of recurrence.
If you have experienced pancreatitis, recurrent upper abdominal pain or complications involving the pancreas or bile ducts, schedule a consultation with a specialist at Tan Siong San Surgery to assess the underlying cause and determine whether further investigation or treatment is appropriate.
Frequently Asked Questions (FAQs)
Is pancreatitis always a medical emergency?
Acute pancreatitis is a potentially serious condition that requires prompt medical assessment, usually in hospital. Not every episode is severe, but complications can develop and the seriousness of the illness may not be clear from symptoms alone.
Where is pancreatitis pain usually felt?
Pancreatitis commonly causes pain in the upper abdomen, often around the centre, which may extend towards the back. The pain can be persistent and severe, although its location and intensity vary between patients.
Can gallstones cause pancreatitis?
Yes. Gallstones are a major cause of acute pancreatitis. A stone passing through or obstructing the bile duct near the pancreatic duct opening can interfere with pancreatic drainage and trigger inflammation.
Can pancreatitis occur without drinking alcohol?
Yes. Pancreatitis has several causes unrelated to alcohol, including gallstones, markedly elevated triglycerides, certain medications, autoimmune conditions and pancreatic duct abnormalities.
How long does acute pancreatitis take to recover from?
Recovery varies according to severity. Many patients with mild acute pancreatitis improve within several days, while severe cases may require weeks or longer in hospital and additional treatment for complications.
Does pancreatitis always require surgery?
No. Most patients receive supportive treatment, including intravenous fluids, pain relief and nutritional support. Surgery or another procedure may be needed to treat gallstones, duct obstruction or selected complications.
Can pancreatitis cause pancreatic cysts?
Pancreatitis can lead to pancreatic pseudocysts, which are encapsulated fluid collections that may develop after pancreatic inflammation. They differ from true cystic pancreatic tumours and do not have the same precancerous potential.
Can pancreatitis cause diabetes?
Yes. Repeated or chronic pancreatic injury can damage cells responsible for producing insulin, potentially leading to diabetes. Some patients may also develop diabetes after a severe episode of acute pancreatitis.
Can you eat normally after pancreatitis?
Many patients with mild acute pancreatitis can resume oral feeding early as tolerated. Dietary advice depends on the severity of the episode, the underlying cause and whether digestive function has been affected. Prolonged fasting is not routinely required.
Can pancreatitis be fatal?
Yes. Severe acute pancreatitis can cause persistent organ failure, infected pancreatic necrosis and other life-threatening complications. However, most patients with mild acute pancreatitis recover with appropriate treatment.
Sun, L., Jiang, M., Wang, X., Sun, Y., Tu, Y., Li, Z., Peng, L., & Huang, H. (n.d.). Etiology, diagnosis, and management of chronic pancreatitis associated primary complications: A narrative review. Frontiers in Medicine, 13, 1822750. https://doi.org/10.3389/fmed.2026.1822750
Kundumadam, S., Fogel, E. L., & Gromski, M. A. (2021). Gallstone pancreatitis: General clinical approach and the role of endoscopic retrograde cholangiopancreatography. The Korean Journal of Internal Medicine, 36(1), 25–31. https://doi.org/10.3904/kjim.2020.537
Chowdhury, P., & Gupta, P. (2006). Pathophysiology of alcoholic pancreatitis: An overview. World Journal of Gastroenterology : WJG, 12(46), 7421–7427. https://doi.org/10.3748/wjg.v12.i46.7421
Fogacci, F., & Cicero, A. F. G. (2026). Hypertriglyceridaemia-associated acute pancreatitis: Risk stratification, drivers, and prevention of recurrence. Diseases, 14(2), 47. https://doi.org/10.3390/diseases14020047
Gieszinger, G., Kui, B., Hegyi, P., Hegyi, P. J., Vincze, Á., Erőss, B., Szentesi, A., Vass, V., Abonyi-Tóth, Z., Izbéki, F., Illés, A., Szabó, I., Czimmer, J., Németh, B. C., Gajdán, L., Papp, M., Hamvas, J., & Czakó, L. (2025). Hypercalcemia causes more severe acute pancreatitis: An international multicenter cohort study. Journal of Clinical Medicine, 14(17), 6304. https://doi.org/10.3390/jcm14176304
Dawod, E., & Kahaleh, M. (2018). Management of benign and malignant pancreatic duct strictures. Clinical Endoscopy, 51(2), 156–160. https://doi.org/10.5946/ce.2017.085
Rashid, M. U., Hussain, I., Jehanzeb, S., Ullah, W., Ali, S., Jain, A. G., Khetpal, N., & Ahmad, S. (2019). Pancreatic necrosis: Complications and changing trend of treatment. World Journal of Gastrointestinal Surgery, 11(4), 198–217. https://doi.org/10.4240/wjgs.v11.i4.198
Yaowmaneerat, T., & Sirinawasatien, A. (2023). Update on the strategy for intravenous fluid treatment in acute pancreatitis. World Journal of Gastrointestinal Pharmacology and Therapeutics, 14(3), 22–32. https://doi.org/10.4292/wjgpt.v14.i3.22
Stamatakos, M., Stefanaki, C., Kontzoglou, K., Stergiopoulos, S., Giannopoulos, G., & Safioleas, M. (2010). Walled-off pancreatic necrosis. World Journal of Gastroenterology : WJG, 16(14), 1707–1712. https://doi.org/10.3748/wjg.v16.i14.1707
This article has been medically reviewed by Dr. Tan Siong San
Dr Tan is a Senior Consultant Surgeon with over 25 years of clinical experience in the field of Hepato-Pancreato-Biliary (HPB) surgery treating conditions affecting gallbladder, liver and pancreas.